
Welcome to the new Tamingthesru
Same great content - new look - improved search
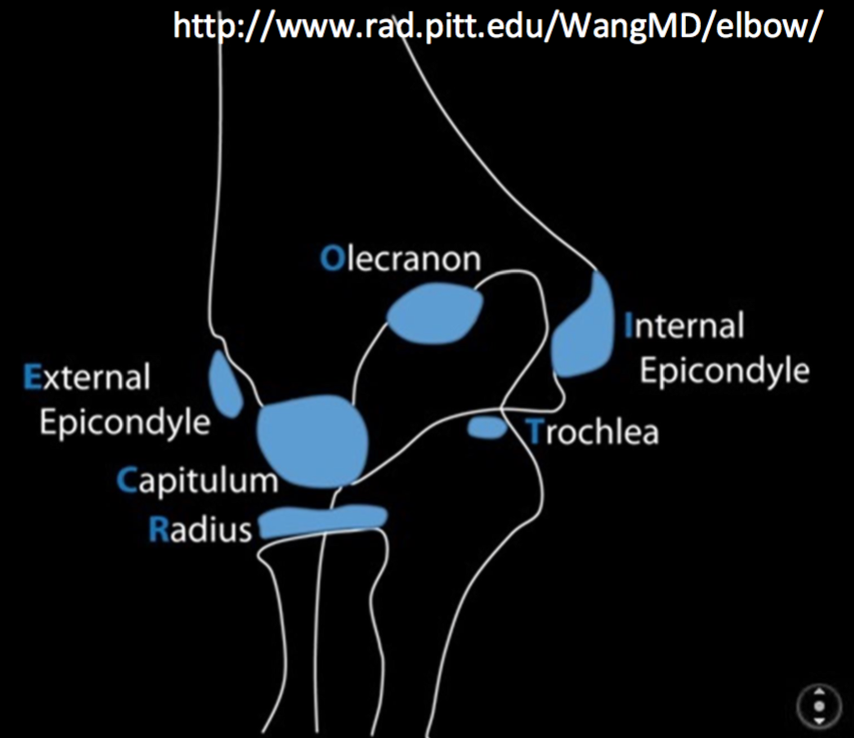
Interpreting Elbow and Forearm Radiographs
Elbow injuries account for 2-3% of all emergency department visits across the nation (1). Yet, because of the elbow’s complex anatomy and the presence of numerous ossification centers in children, elbow fractures are the third most commonly missed fracture group in the ED (1). Here are some tools to help ED physicians read elbow x-rays more effectively and hopefully identify abnormalities more easily...

Thoracentesis
General Considerations
Both the diagnostic and therapeutic thoracenteses are performed using a similar technique. The major difference is the amount of fluid removed. The proceduralist may also choose to only use the needle technique as opposed to the needle-catheter unit when obtaining fluid for diagnostic purposes only.
It is generally recommended that needle size be limited to 18-gauge or smaller to minimize risk of pneumothorax and damage to nearby structures.
US-guided thoracentesis is associated with a significantly lower rate of complications and has become the standard of care. (1) Real-time ultrasound (US) guidance is recommended for small or loculated effusions when there is concern that the diaphragm or lung tissue is <10mm from the pleural surface. It is also recommended in patients with relative contraindications such as coagulopathies and the mechanically ventilated patient.

Lung Ultrasound: Evaluation for Pleural Fluid and Pneumothorax
The Basics
Think about gravity: fluid will collect in most dependent region (down); air tends to collect towards the least dependent regions (up)
Air does not reflect sound waves well. Lungs are filled with air. Rather than getting most of our information from visualizing the anatomy (as in a RUQ ultrasound, for example), much of our information comes from “artifact” or ultrasound waves being affected by phase changes.