
Welcome to the new Tamingthesru
Same great content - new look - improved search

Is a STEMI a STEMI in Post-ROSC Patients?
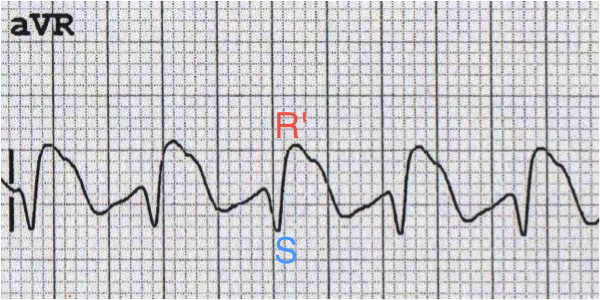
One of the first tests ordered for a patient with ROSC following cardiac arrest is an EKG. Many of these EKGs are profoundly abnormal. Current practice is to evaluate for STEMI and to activate the cardiac cath lab if one is found. But, the test characteristics (sensitivity and specificity) of post-ROSC EKGs are likely different than the test characteristics for patients presenting to the ED with complaints of chest pain/symptoms concerning for ACS. This meta-analysis looked to pull together the existing literature and determine those test characteristics for this critically ill patient population. Read the summary after the link and listen to the podcast to hear a breakdown of this study.

Is the Cath Lab the Place to be after V fib VTac Cardiac Arrest?
Ventricular dysrhythmias are commonly caused by coronary ischemia which is most frequently caused by acute coronary artery occlusions in the setting of coronary artery disease. It would seem somewhat logical that patients who suffer a V fib or V Tach cardiac arrest would benefit from a trip to the cardiac catheterization lab to identify and treat these possible acute coronary artery occlusions. Patient’s with EKGs showing ST-elevations following ROSC already go to the Cath lab. Since the EKG is not terrifically sensitive for MI, should V fib V Tach cardiac arrest patients without ST-elevations make a trip to the Cath lab? In this breakdown of our most recent journal club we look at several papers covering this topic. In the podcast below we also talk with Justin Benoit, MD the site PI for the ongoing ACCESS trial which is also looking into this question.
Grand Rounds Recap 10/14
Simulation with Dr. Hill
Case 1: 45 yo male comes to the ED after being found down at the mall s/p defib x2 for a V fib arrest per EMS with a King Airway in place and undergoing active CPR. In the ED you achieve ROSC after defib x1 for Vfib and then PEA with multiple arounds of epinephrine. EKG shows inferior STEMI.
Case 2: EMS calls with advanced noticed for GI bleed presents tachycardic and hypotensive, actively bleeding with melanotic stool and hematemesis.