
Welcome to the new Tamingthesru
Same great content - new look - improved search
Grand Rounds Summary 3/2/16
OB-GYN Emergencies with Dr. McKinney
Case 1: 18 wk patient with vaginal spotting who is Rh- but antibody+
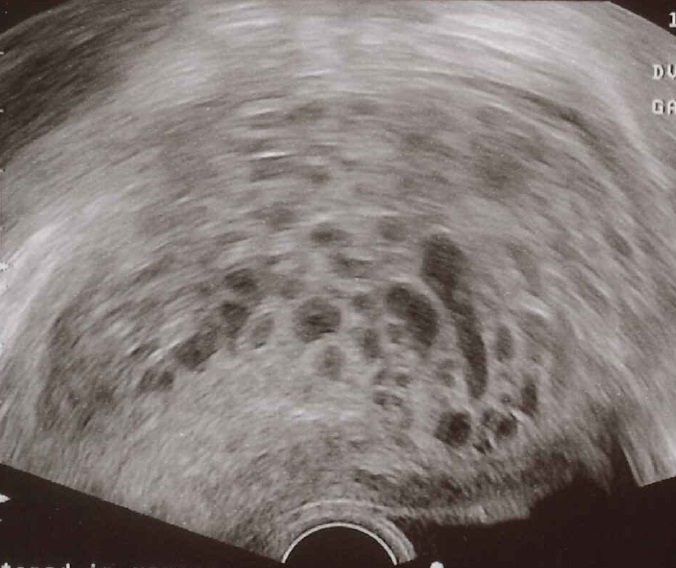
Bedside U/S shows fetal abnormality due to Rh alloimmunization with fetal hydrops. Positive antibody screening on gravid female should warrant obstetric consultation. Rhogam administration within 72 hours of bleeding is important.
Case 2: 40 wk female with gestational DM present with crowning fetus who fails to immediately deliver secondary to shoulder dystocia.
Treatment: stop pushing and avoid traction. Initially attempt hyperflexion of legs and suprapubic pressure to release (McRoberts maneuver). Then consider episiotomy because subsequent maneuvers involve twisting the baby to get shoulder into a different plane.

Lung Ultrasound: Evaluation for Pleural Fluid and Pneumothorax
The Basics
Think about gravity: fluid will collect in most dependent region (down); air tends to collect towards the least dependent regions (up)
Air does not reflect sound waves well. Lungs are filled with air. Rather than getting most of our information from visualizing the anatomy (as in a RUQ ultrasound, for example), much of our information comes from “artifact” or ultrasound waves being affected by phase changes.
Closing the Gap: Deep Sutures
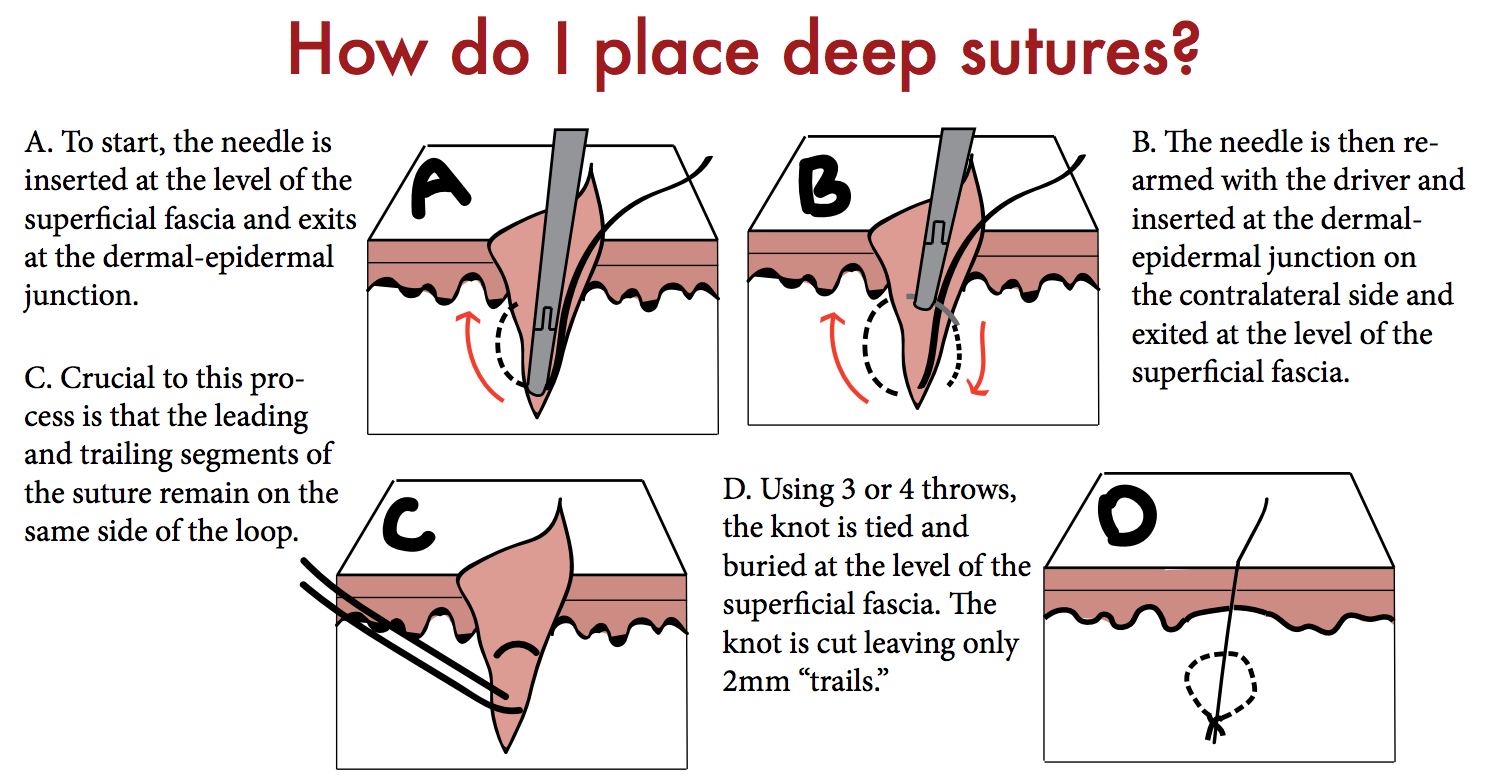
While many wounds are adequately repaired with simple interrupted sutures, not infrequently we are confronted with wounds that require more specialized suturing methods. One such method is deep sutures. Here to answer some questions regarding deep sutures is our wound management guru, and author of the book “Wounds and Lacerations: Emergency Care and Closures,” Dr. Alexander Trott.